



“Diagnoses are sometimes entered into medical records without…meaningful consideration of medically authorized cannabis use.”
By Etienne Fontan, Veterans Action Council
The 2013 release of the Diagnostic and Statistical Manual of Mental Disorders (DSM-5) introduced cannabis use disorder (CUD) as a new diagnosis, replacing the DSM-4 categories of Cannabis Abuse and Cannabis Dependence with a single, severity-based unified diagnosis.
This change was framed as a modernization of psychiatric classification, but it has had significant implications within systems such as the Veterans Health Administration (VHA) under the U.S. Department of Veterans Affairs (VA).
In Part 4 of our series on veterans’ cannabis issues that are illuminated by the Veterans Action Council’s (VAC) Freedom of Information Act (FOIA) request, we turn our focus toward a problem affecting many veterans: the improper diagnosis of CUD within VHA.
CUD is defined as a pattern of cannabis use that causes clinically significant impairment or distress, assessed through criteria including impaired control, cravings, continued use despite harm, tolerance and withdrawal. The DSM-5 places these criteria on a continuum, classifying severity as mild, moderate or severe according to the number of criteria met.
However, the decision by the American Psychiatric Association (APA) to merge cannabis abuse and dependence into a single diagnosis did more than streamline terminology. It fundamentally altered the threshold and breadth of diagnosis.
Under DSM-IV, abuse and dependence were distinct conditions with different clinical implications. Abuse generally referred to problematic patterns of use with social or legal consequences, while dependence suggested a more entrenched physiological and behavioral pattern.
By collapsing these into one category, DSM-5 widened the diagnostic net, capturing a broader range of individuals under a single label.
This shift was driven by concerns about inconsistency. Researchers and clinicians had long observed that the boundary between abuse and dependence was not always clear and that patients often moved between categories. DSM-5 sought to resolve this by treating substance use as a spectrum.
In theory, this improved diagnostic reliability and aligned cannabis with other substance use disorders. In practice, however, it also created circumstances in which individuals who previously would not have received a diagnosis or would have received a less severe diagnosis could now be classified as having a disorder.
This distinction is not merely academic. A diagnosis carries weight. It shapes treatment decisions, becomes part of a patient’s permanent medical record and influences how future providers interpret that patient’s history.

Within the VHA system, the broader definition of CUD has intersected with institutional practices in ways that many veterans and advocates find troubling.
Reports have surfaced describing situations in which a positive THC test, often obtained through routine screening, is followed by the assignment of a CUD diagnosis without a comprehensive clinical evaluation.
Such practices raise an important question: Is CUD always being applied as a carefully considered medical diagnosis, or has it, in some cases, become an administrative label? In a proper clinical setting, diagnosis should follow a thorough assessment that considers symptoms, context, medical history and the patient’s own explanation of their cannabis use.
It should involve a conversation in which the patient understands the criteria being applied and has an opportunity to explain whether their cannabis use is therapeutic, medically supervised or otherwise clinically appropriate.
Yet many veterans report that this process is not consistently followed. Diagnoses are sometimes entered into medical records without prior discussion, without documentation of a structured DSM-5 assessment and without meaningful consideration of medically authorized cannabis use.
This gap between diagnostic standards and real-world application undermines the principles DSM-5 was intended to advance. When patients use cannabis daily under state medical cannabis laws to manage chronic pain, PTSD or other conditions, they may satisfy certain DSM criteria despite experiencing improved functioning rather than impairment.
Cannabis occupies a uniquely complex position within American healthcare. Although it remains federally prohibited, it is legal for medical use in many states and is widely used by veterans seeking alternatives to opioids or other medications.
The DSM-5 framework does not explicitly distinguish therapeutic cannabis use from problematic use. As a result, individuals using cannabis as physician-guided symptom management may nevertheless fall within a diagnostic framework originally intended to identify psychiatric illness.
The consolidation of abuse and dependence into a single diagnosis has also contributed to what many describe as diagnostic inflation. When criteria are broadened and applied without careful clinical judgment, prevalence rates may increase—not necessarily because more patients have a true disorder, but because more individuals satisfy an expanded definition.
In large systems such as VHA—where diagnostic coding serves administrative, research and reporting functions—this creates the risk that consistency may take precedence over individualized assessment.
The role of institutions cannot be overlooked. The APA establishes diagnostic criteria, but organizations such as the VHA operationalize those criteria on a national scale. Their implementation determines how these definitions affect veterans’ lives.
The increasing emphasis on CUD within the VHA system has coincided with expanded drug screening practices and a historically cautious institutional approach toward cannabis. What has not kept pace, however, is the rapid evolution of scientific research examining both the potential therapeutic benefits and the limitations of medical cannabis.
None of this is to suggest that CUD is not a legitimate diagnosis. For some individuals, cannabis use becomes harmful and requires clinical intervention. The concern is not the diagnosis itself, but proportionality, accuracy and adherence to accepted diagnostic standards.
Additional Evidence From VAC FOIA Records
Internal VA records obtained through the VAC’s FOIA request raise important questions about how VHA applies CUD. In 2022, VA correspondence reported 134,790 veterans with cannabis-positive urine drug screens and 139,336 veterans identified as having CUD. While these figures alone do not prove improper diagnoses, they warrant scrutiny when compared with national epidemiologic data.
Research cited within the same FOIA records from the National Epidemiologic Survey on Alcohol and Related Conditions (NESARC-III) found that 7.3 percent of U.S. veterans reported cannabis use in the previous year, but only 1.8 percent met DSM criteria for CUD. This suggests that only a minority of cannabis users meet the diagnostic threshold and underscores the need for individualized clinical assessments rather than reliance on cannabis use alone.
The FOIA records also reveal that VA officials recognized the complexity of the issue.
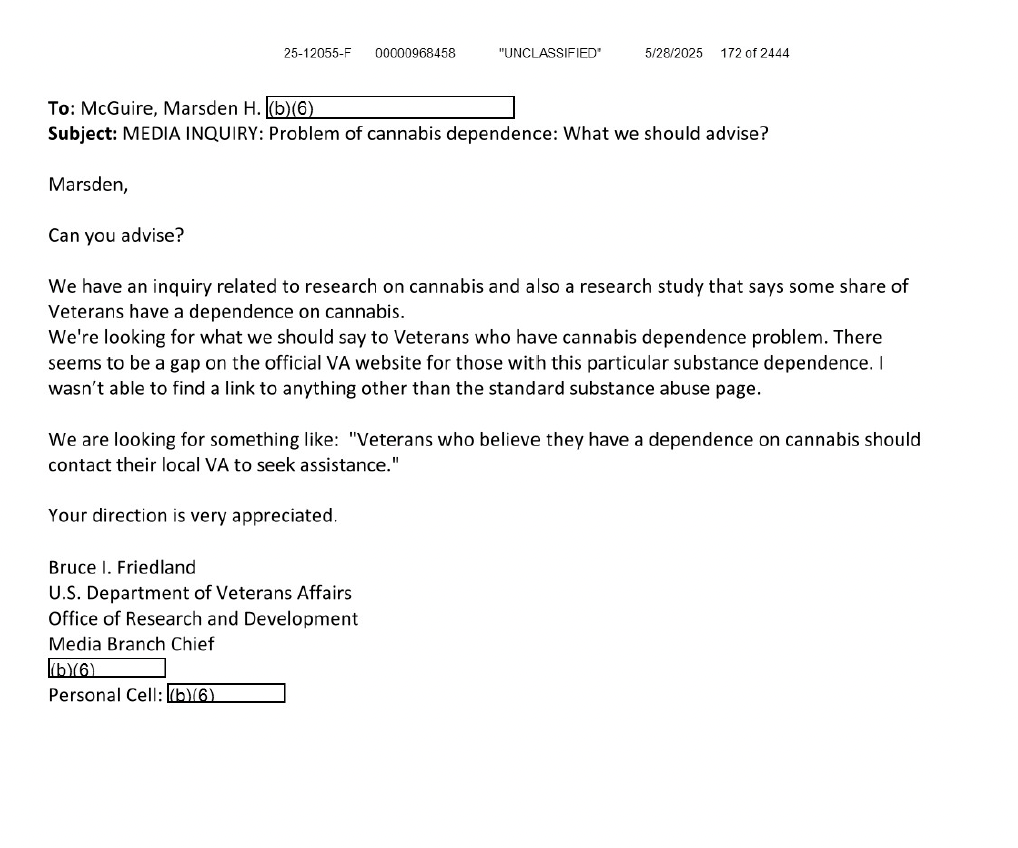
In one email, VA Office of Research and Development Media Branch Chief Bruce I. Friedland acknowledged the need to “thread a needle” between addressing genuine cannabis-related substance use disorders and supporting research into cannabis as a potential therapeutic treatment.

In another email, Friedland sought guidance because VA lacked cannabis-specific resources for veterans who believed they had developed cannabis dependence.
Additional correspondence from UCSF physician Dr. Salomeh Keyhani recommended that veterans identified through urine drug screening be individually assessed for high-risk cannabis use and offered treatment when appropriate, consistent with the DSM-5 requirement for a comprehensive clinical evaluation rather than diagnosis based solely on laboratory findings.

VA research contained in the FOIA materials also found that nearly one third of reviewed patient records contained no documented discussion of cannabis between providers and patients. Of those that did, nearly half involved medical cannabis use rather than discussions of risks or harm reduction.
These findings reinforce the importance of patient-provider dialogue and individualized clinical judgment before assigning a psychiatric diagnosis.
For veterans managing complex medical conditions, inaccurate psychiatric diagnoses can affect treatment decisions, disability evaluations, provider perceptions and confidence in the medical record. Restoring integrity to CUD diagnosis requires rigorous application of DSM-5 criteria, informed patient participation, consideration of therapeutic cannabis use and periodic review of institutional practices to ensure administrative efficiency never replaces sound clinical judgment.
A diagnosis should ultimately serve the patient by guiding treatment and accurately reflecting clinical reality. The value of DSM-5 depends not only on how its criteria are written, but on how faithfully they are applied.
Etienne Fontan is a U.S. Army Desert Storm combat veteran and co-owner of Berkeley Patients Group, one of the nation’s longest-operating medical cannabis dispensaries. He serves on the Veterans Action Council, where he works on veterans’ access to cannabis, federal policy reform and international drug policy issues.
